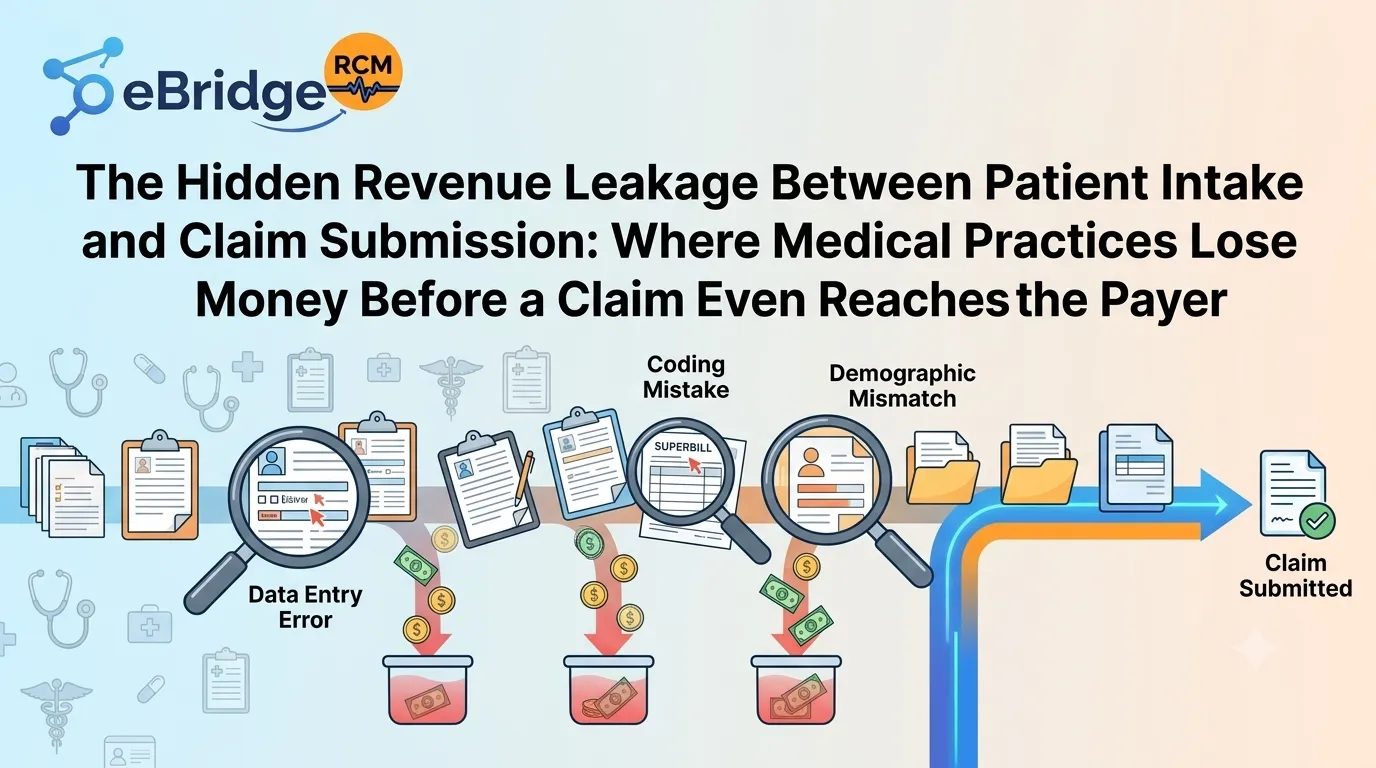

A medical claim can fail long before an insurance company sees it. The problem often starts during patient intake, registration, eligibility checks, or charge capture. Small mistakes made at these early stages can follow a claim through the entire revenue cycle. By the time the billing team spots the issue, the practice may already have lost time, delayed payment, or written off revenue.
This problem affects practices of all sizes. A busy front desk may enter the wrong insurance ID. A patient may provide an outdated address. A provider may document a service without enough detail to support the selected code. A payer may require authorization that nobody checked before the appointment. Each issue looks minor on its own. Together, they can create a steady stream of avoidable revenue loss.
Practices that provide care across different markets also face payer-specific rules and administrative requirements. For example, organizations looking for specialized medical billing services in New York often need strong processes for eligibility, claim preparation, payer follow-up, and denial management. The earlier a billing issue is found, the easier it usually is to correct.
Where Revenue Leakage Begins Before Claim Submission
Revenue leakage does not always look like a denied claim. Sometimes it appears as a claim that was never created correctly. Other times, it appears as a payment that comes in lower than expected.
Patient intake is one of the first points where financial information enters the revenue cycle. The information collected at this stage influences eligibility, claim routing, patient responsibility, coding, and payer communication.
Consider a patient who changes insurance but does not update their information before an appointment. The practice submits the claim using the old payer details. The claim comes back as inactive coverage. Staff members then spend time researching the account, contacting the patient, checking eligibility, and resubmitting the claim.
The practice may eventually receive payment. However, the revenue cycle has already absorbed extra labor and lost valuable time.
Common sources of leakage between intake and claim submission include:
- Incorrect insurance member IDs
- Expired or incomplete insurance information
- Missing subscriber details
- Incorrect patient demographics
- Duplicate patient records
- Missing authorization or referral information
- Incorrect payer selection
- Incomplete provider enrollment information
- Missing documentation
- Coding that does not match the clinical record
- Charges that were never captured
- Services entered under the wrong provider or location
- Claims submitted outside payer-specific requirements
These problems can also create downstream effects. A demographic error can cause a claim rejection. A missing authorization can result in a denial. An incomplete clinical note can make a properly performed service difficult to support during an audit or payer review.
The Cost of Small Errors Adds Up
Revenue leakage becomes more serious when a practice treats each error as an isolated event.
Suppose a practice submits 2,000 claims each month. If only a small percentage require manual correction, staff can still spend hundreds of hours each year fixing preventable issues. The financial impact includes more than the unpaid claim.
There is staff time spent reviewing accounts. There are phone calls with patients and insurers. There are resubmissions. There may also be delayed cash flow when claims sit unresolved.
The practice can lose revenue in several ways:
Delayed reimbursement: A claim that needs correction takes longer to reach adjudication.
Lost reimbursement: Some claims never get corrected within the payer's filing deadline.
Underpayments: Incorrect information can affect how a payer processes or prices a claim.
Higher administrative costs: Billing staff spend time fixing issues that could have been prevented during registration.
Patient collection problems: Incorrect insurance information can cause balances to be assigned to patients incorrectly.
This is why revenue cycle performance should not focus only on the final claim denial rate. A practice needs to examine what happens before the claim reaches the clearinghouse and payer.
Patient Intake and Eligibility Verification Need More Than Data Entry
Patient registration should not be treated as a basic administrative task. It forms the financial foundation of the encounter.
A strong intake process verifies information instead of simply collecting it. Staff should confirm the patient's name, date of birth, address, insurance details, subscriber relationship, member ID, group number, and other required information.
Eligibility verification adds another layer. It helps determine whether coverage is active and whether the planned service falls within the patient's benefits. Depending on the payer and service, the practice may also need to confirm authorization, referral requirements, network status, or other restrictions.
Timing matters as well. Checking eligibility weeks before an appointment may not provide enough confidence if coverage changes before the date of service. Practices need workflows that fit the type of care they provide and the payer mix they handle.
Automation can help, but technology does not replace process ownership. Someone must still review exceptions and act on information that requires clarification.
Charge Capture and Documentation Can Create Another Gap
Even when registration and insurance information are correct, revenue can disappear during charge capture.
A provider performs a service, but the charge does not make it into the billing system. Or the service is entered with the wrong code. In another case, documentation may not fully support the billed service.
These issues create a disconnect between what happened during the encounter and what reaches the payer.
Accurate coding depends on the medical record. Coding teams must work from the provider's documentation and apply the appropriate coding rules. They should not add unsupported details simply to increase reimbursement.
Practices should also watch for services that commonly fall through the cracks. Lab services, procedures, supplies, injections, prolonged services, and other billable items may require specific workflows. A missing charge can be just as damaging as an incorrect charge.
How Practices Can Reduce Leakage Before Claims Go Out
The best approach is to find problems closer to their source.
Start by mapping the patient journey from scheduling through claim submission. Identify every point where information changes hands. Then ask what can go wrong at each step.
A practical review should include:
- Registration accuracy: Check how demographic and insurance data enters the system.
- Eligibility checks: Track when verification happens and how exceptions are handled.
- Authorization controls: Identify services that require prior authorization or referrals.
- Charge reconciliation: Compare scheduled services, clinical documentation, and charges.
- Coding review: Look for recurring coding errors and documentation gaps.
- Claim scrubbing: Review claims for missing or conflicting information before submission.
- Rejection tracking: Separate registration-related rejections from coding and payer issues.
- Staff feedback: Ask front-office and billing teams where they repeatedly see the same problems.
Data can reveal patterns that individual account reviews may miss. For example, if most rejected claims come from one payer or one registration location, the issue may be tied to a specific workflow rather than overall billing performance.
Build a Revenue Cycle That Finds Problems Early
A healthy revenue cycle is not simply about sending more claims. It is about sending accurate claims with the right information at the right time.
Leadership should monitor metrics across the entire process. Useful measures include clean claim rate, first-pass acceptance, eligibility-related rejections, authorization denials, charge lag, coding-related denials, days in accounts receivable, and net collection rate.
These metrics should be reviewed together. A high clean claim rate may look positive, but it does not tell the whole story if the practice is missing charges before claims are created.
Staff training also deserves attention. Front-desk teams need to understand why accurate registration matters. Providers need clear documentation expectations. Coding and billing teams need current payer guidance and consistent escalation procedures.
When every department understands its part of the revenue cycle, fewer problems are passed to the next stage.
Turn the Gap Between Intake and Billing Into a Control Point
The space between patient intake and claim submission is easy to overlook. It sits between clinical care and reimbursement, so responsibility can become fragmented. Front-desk staff handle registration. Providers handle documentation. Coders review services. Billers prepare claims. Each team may do its job while the overall process still leaks revenue.
The answer is to connect those functions.
Practices should treat every patient encounter as a financial record that needs accurate information from beginning to end. Early verification, reliable documentation, careful charge capture, payer-specific claim checks, and regular performance reviews can prevent many avoidable problems.
Revenue leakage rarely comes from one dramatic mistake. More often, it develops through dozens of small gaps that repeat every week. Finding those gaps before the claim leaves the practice can protect cash flow, reduce administrative work, and improve the patient billing experience.
If your practice needs help identifying these gaps, eBridge RCM can support the full revenue cycle, from patient intake and eligibility verification to coding, claim submission, denial follow-up, and payment management. For behavioral health providers seeking specialized support, explore our Mental Health Billing Services NYC and see how a structured billing process can help reduce preventable revenue loss.


























Sign in to leave a comment.