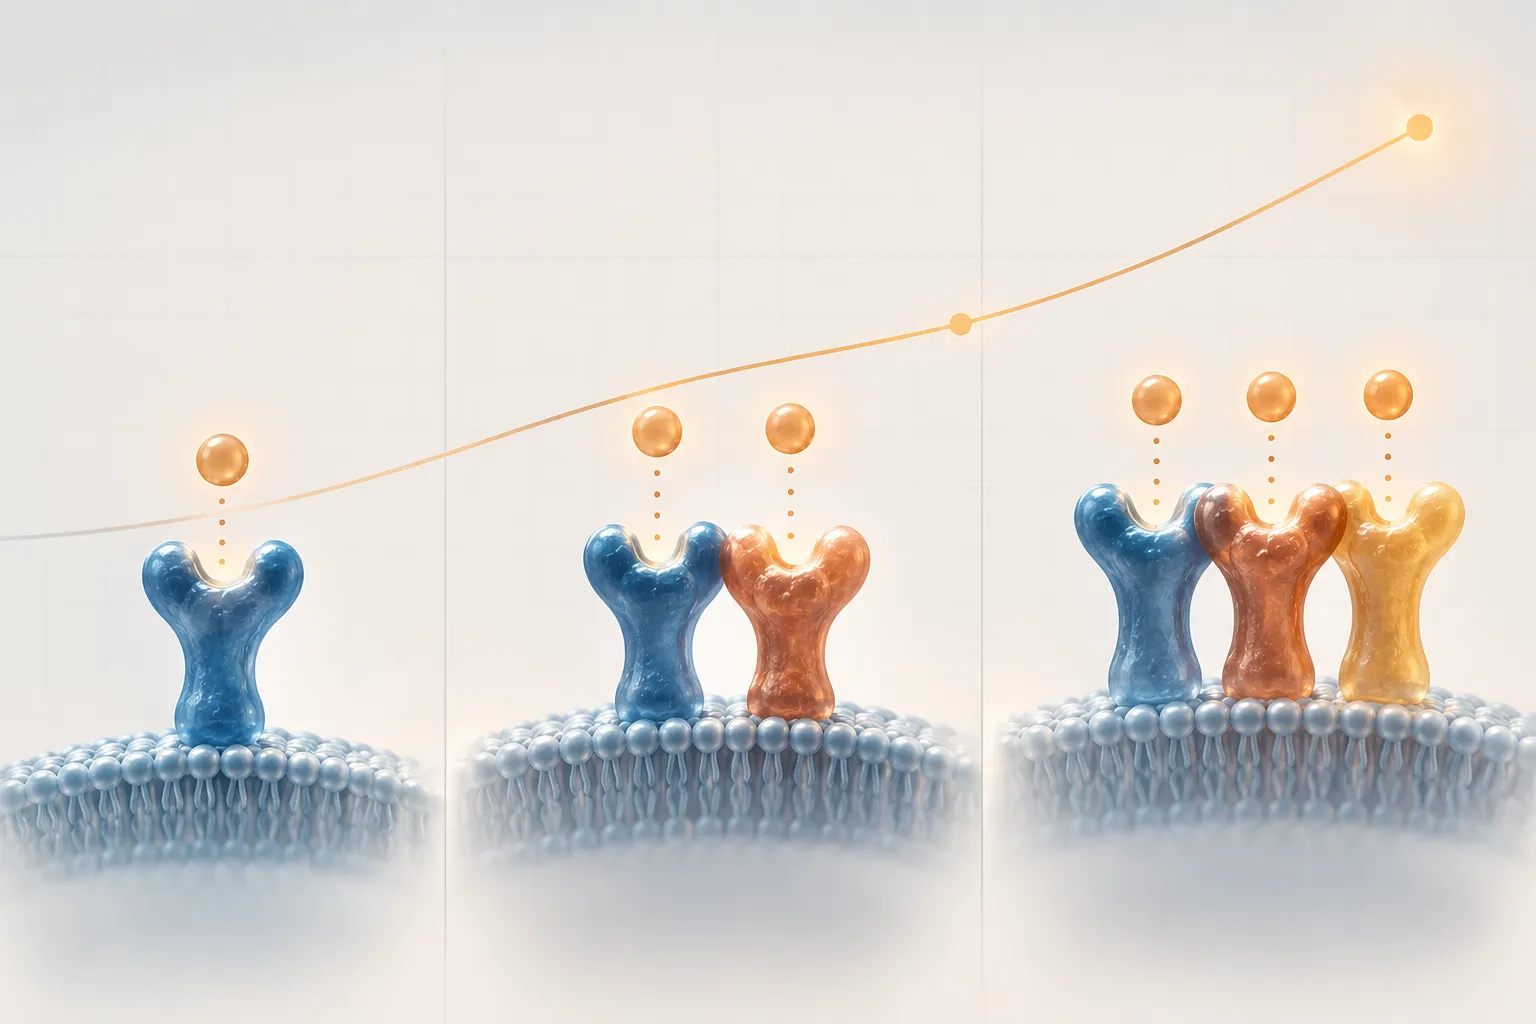

Semaglutide, tirzepatide, and retatrutide get talked about like three versions of the same story — bigger numbers, same category. That's mostly true, but the actual trial data behind each one is more specific, and more different, than the shorthand suggests. Here's what each one has actually shown, and where each one genuinely stands.
The Core Idea: Stacking Receptors
All three drugs work through the same general family of gut-hormone signaling, but each targets a different number of receptors:
- Semaglutide activates a single receptor: GLP-1, which slows digestion, increases feelings of fullness, and improves insulin response.
- Tirzepatide is a dual agonist, adding GIP receptor activation alongside GLP-1 — a second hormone pathway involved in insulin sensitivity and fat metabolism.
- Retatrutide goes a step further as a triple agonist, adding glucagon receptor activation on top of GIP and GLP-1 — a pathway that increases energy expenditure, at the cost of a more complex side-effect profile.
The Actual Trial Numbers
Semaglutide — STEP 1 trial (Wilding et al., NEJM, 2021): a large, randomized, placebo-controlled trial that demonstrated substantial, sustained weight loss over 68 weeks, becoming the result that first proved a peptide could meaningfully compete with, and outperform, prior generations of weight-management drugs.
Tirzepatide — SURMOUNT-1 trial (Jastreboff et al., NEJM, 2022): a 2,539-participant Phase 3 trial found average weight reductions of up to 22.5% at the highest (15 mg) dose over 72 weeks, compared to 3.1% on placebo — meeting both co-primary endpoints with statistical significance (P<0.001).
Retatrutide — Phase 2 trial (Jastreboff et al., NEJM, 2023): the highest-dose group showed weight reduction substantially exceeding both prior drugs at a comparable timepoint, with later trial data (reported in 2026) showing average losses as high as 28.3% of body weight at 80 weeks in the highest-dose group — the largest figure of the three, but still from a Phase 3 program, not a completed and approved drug.
More Receptors Isn't Automatically "Just Stronger"
It's tempting to read this as a simple ladder — one receptor, two receptors, three receptors, bigger number each time — but each additional receptor changes the side-effect profile too, not just the effect size. The glucagon receptor component unique to retatrutide, for instance, is associated with a mild increase in heart rate not seen with the single- and dual-agonist drugs — a real, distinct consideration that a bigger headline weight-loss number doesn't capture on its own.
Where Each One Actually Stands
This is the part that matters most if you're evaluating any of these beyond the trial results:
- Semaglutide is FDA-approved for chronic weight management under the brand name Wegovy, following its 2021 trial data.
- Tirzepatide is FDA-approved for chronic weight management under the brand name Zepbound, approved in November 2023 following SURMOUNT-1.
- Retatrutide remains in Phase 3 trials, with an FDA filing expected in early 2027. It is not approved anywhere, and — as covered elsewhere in this series — that gap has fueled a black-market supply of unregulated "research-use-only" retatrutide that Eli Lilly is currently suing over.
The Honest Summary
The trial data genuinely does show an escalating effect as more receptors get added to the mechanism — that part isn't hype. But "produced the biggest number in a trial" and "approved, manufactured under regulatory oversight, and available through a legitimate pharmacy" are two completely separate facts, and right now only two of these three drugs can claim both. The size of a weight-loss percentage in a headline is not a substitute for checking which of these three actual situations a given compound is in.
For more compounds documented at this level of trial-stage detail, Peptide AtlasX catalogs research peptides with citations back to the underlying published studies.












Sign in to leave a comment.