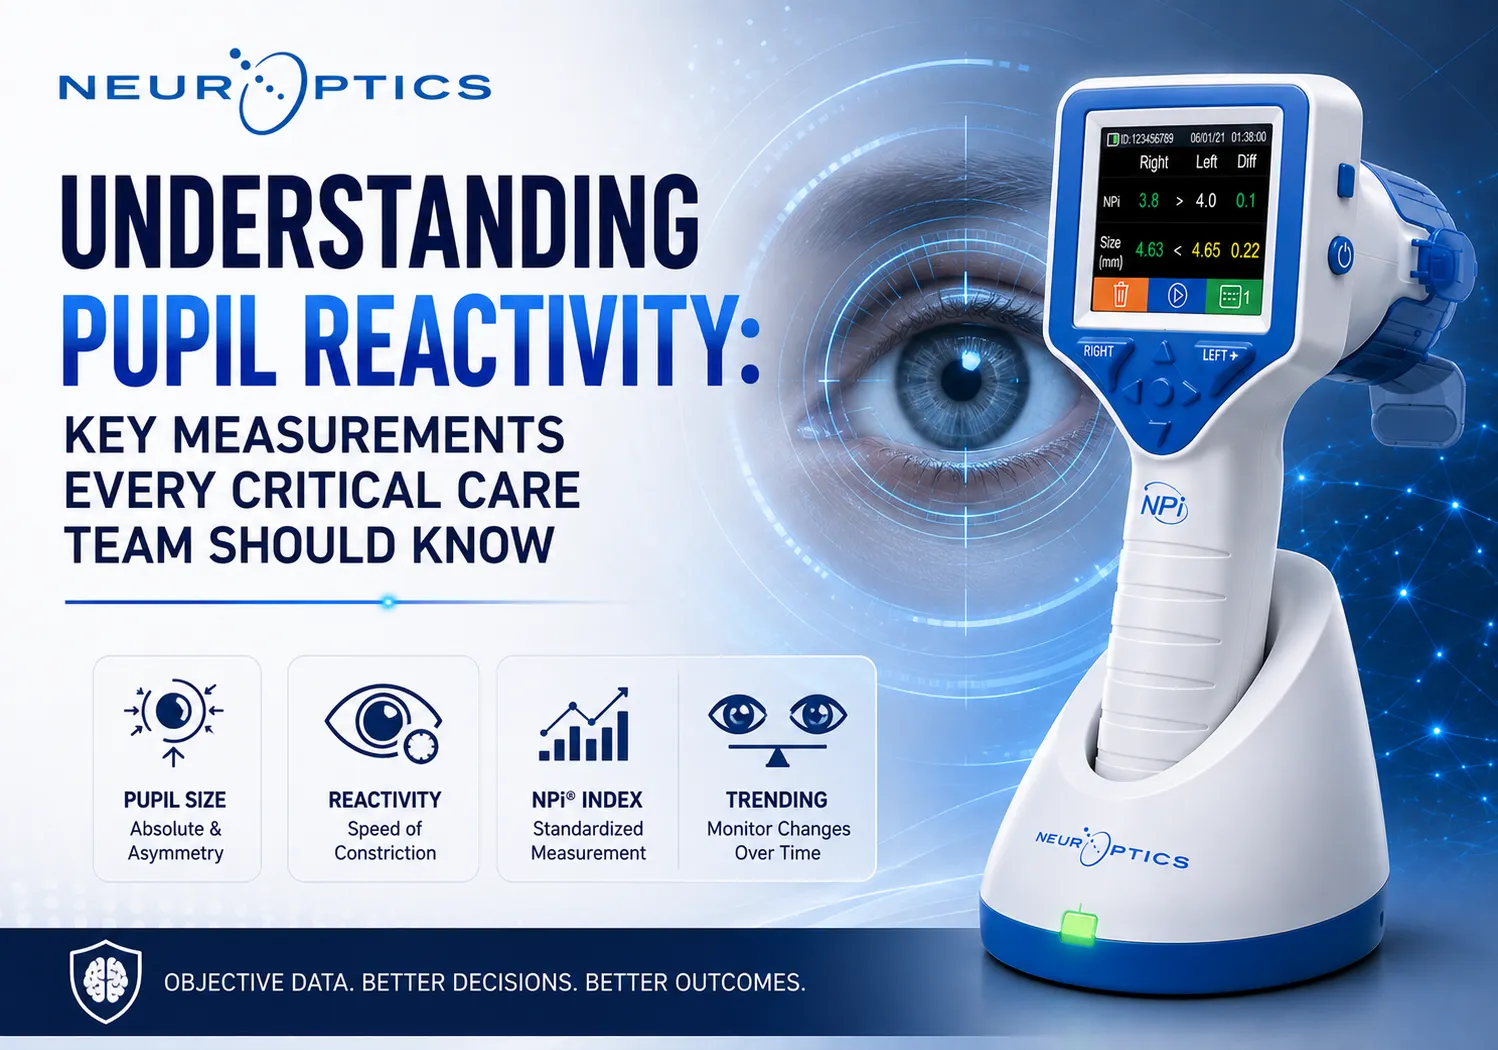

A pupil reacting a little slower than it did an hour ago can be the earliest sign of trouble in a critically ill patient, often before blood pressure or heart rate change. The measurements that matter most are pupillary size, the percent change in pupil size after light exposure, and how fast the pupil constricts. Together, these numbers show whether the pupillary light reflex is working correctly, not just whether the pupil moves.
Pupils have been part of the bedside neuro exam for as long as clinicians have carried a penlight. What has changed is how precisely that exam can now be done.
Why Pupillary Size Measurement Alone Isn't Enough
Estimating pupil size by eye, even with a gauge card, leaves room for error. In one study, when a pupillometer measured constriction below its 15 percent reactivity threshold, examiners often still recorded the pupil as reactive, missing a reduced response the device caught automatically. A separate interrater study found that when pupillometer readings confirmed non-reactive pupils, practitioners agreed with those readings only 55 to 70 percent of the time, depending on the examiner. A pupil that looks “normal” in size can still have an abnormal reflex once light response is measured.
What Percent Change in Pupil Size Reveals
The change in pupil size after light stimulation shows how much the pupil constricts relative to its resting diameter. This number often reveals a weakening light reflex before size or shape change on their own, since reactivity changes under 15 percent are exactly the range manual exams tend to miss.
Constriction Velocity: What a Penlight Can't Capture
No manual exam can time how fast a pupil moves. This measurement, in millimeters per second, is generally considered abnormal below 0.8 mm/sec. A pupil can look briskly reactive to the eye while its actual speed falls into an abnormal range, part of why an automated reading captures more than tradition alone.
Expert Insight
Clinicians who use pupillometry daily point to one rule newer users often overlook: no single number should be read alone. A normal size paired with a slow constriction speed still signals a reflex worth watching.
| Measurement | What It Captures | Reference Range |
|---|---|---|
| Pupil Size (mm) | Resting pupil diameter | About 2–4 mm in bright light, up to 8 mm in darkness; varies by individual and lighting |
| Percent Change in Pupil Size | Reduction in diameter after light stimulus | Changes under 15% are frequently missed on manual exam |
| Constriction Velocity (mm/sec) | Speed of pupil constriction | Below 0.8 mm/sec is considered abnormal |
| NPi® | Composite score from a validated normative model | 3.0–4.9 is normal; below 3.0 is abnormal; 0 indicates non-reactivity |
How NPi® Changes the Neuro Exam
It replaces subjective terms like “brisk” and “sluggish” with a numeric score built from a normative model of the light reflex. A difference of 0.7 or more between the left and right eye's score signals possible neurological change. NPi® and automated pupillometry are now part of the 2020 American Heart Association resuscitation guidelines for prognostication after cardiac arrest.
How to Use a Pupillometer in Daily Practice
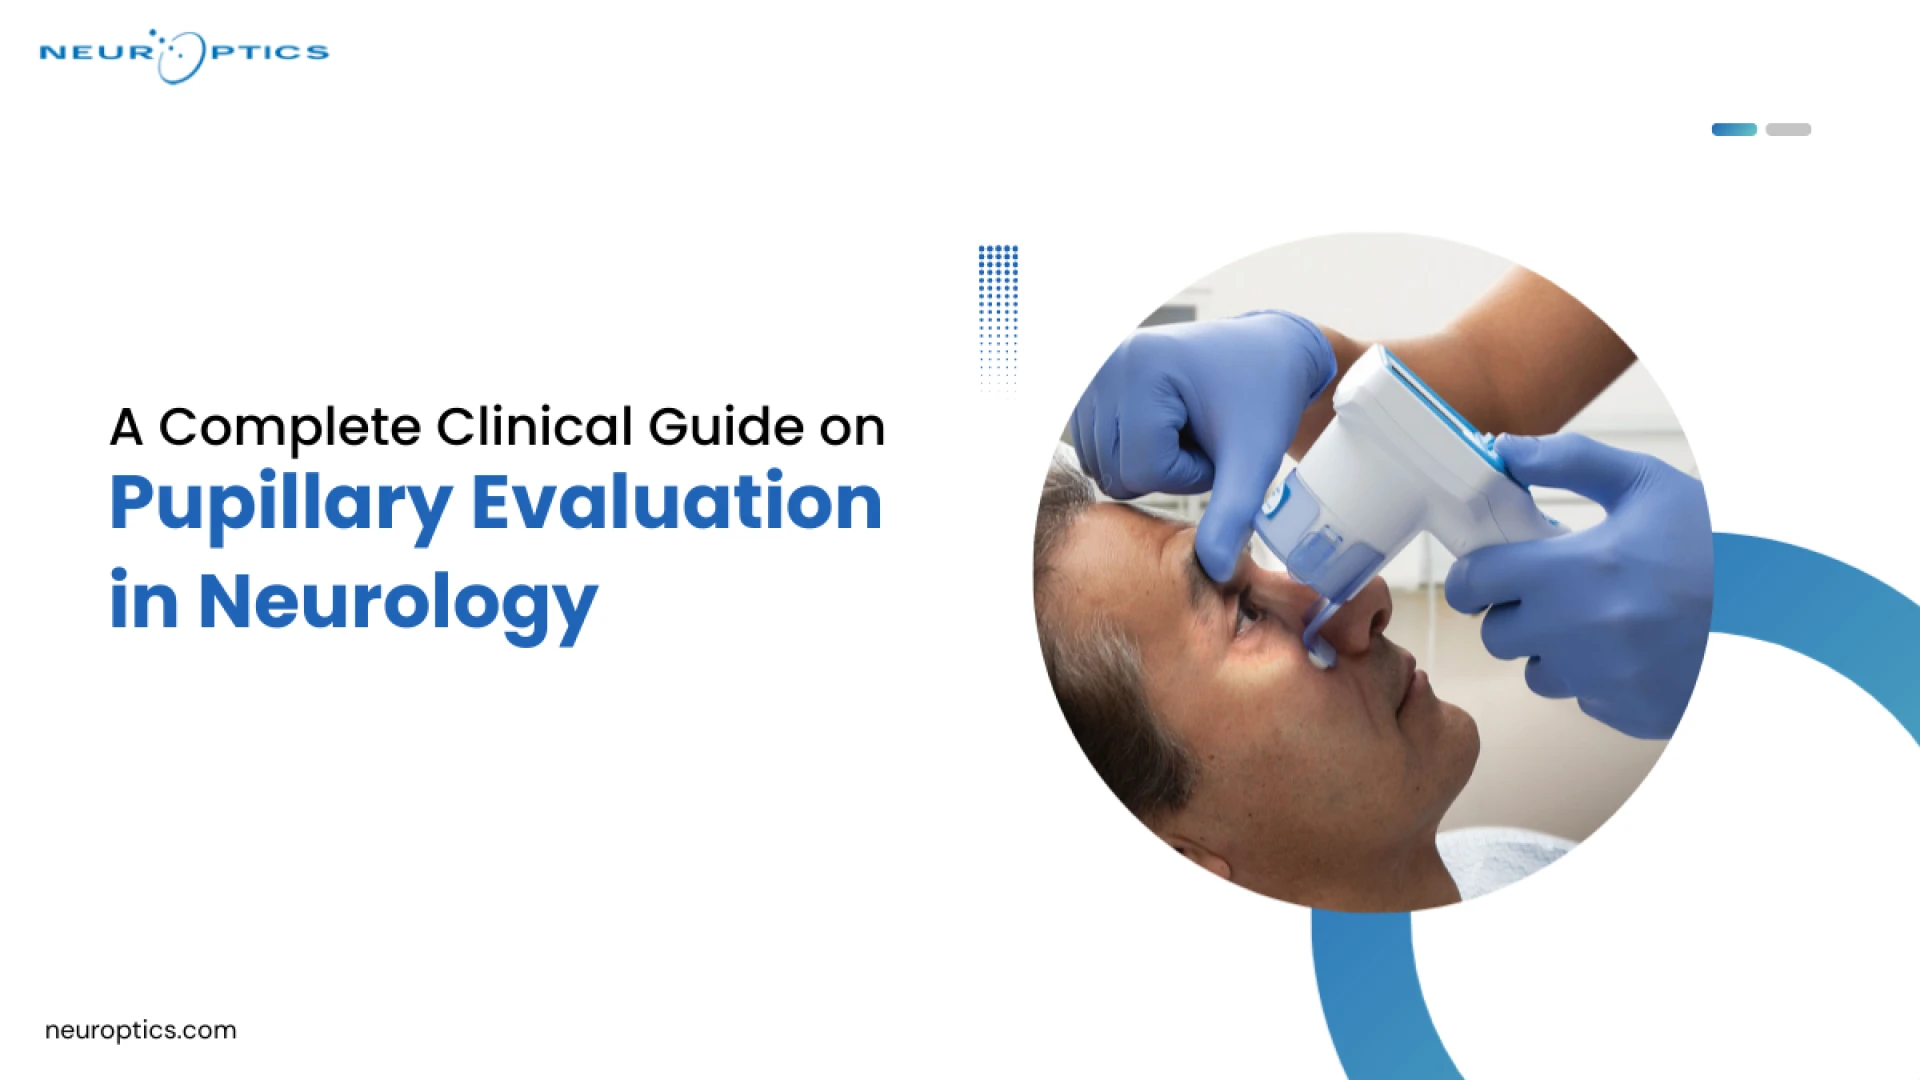
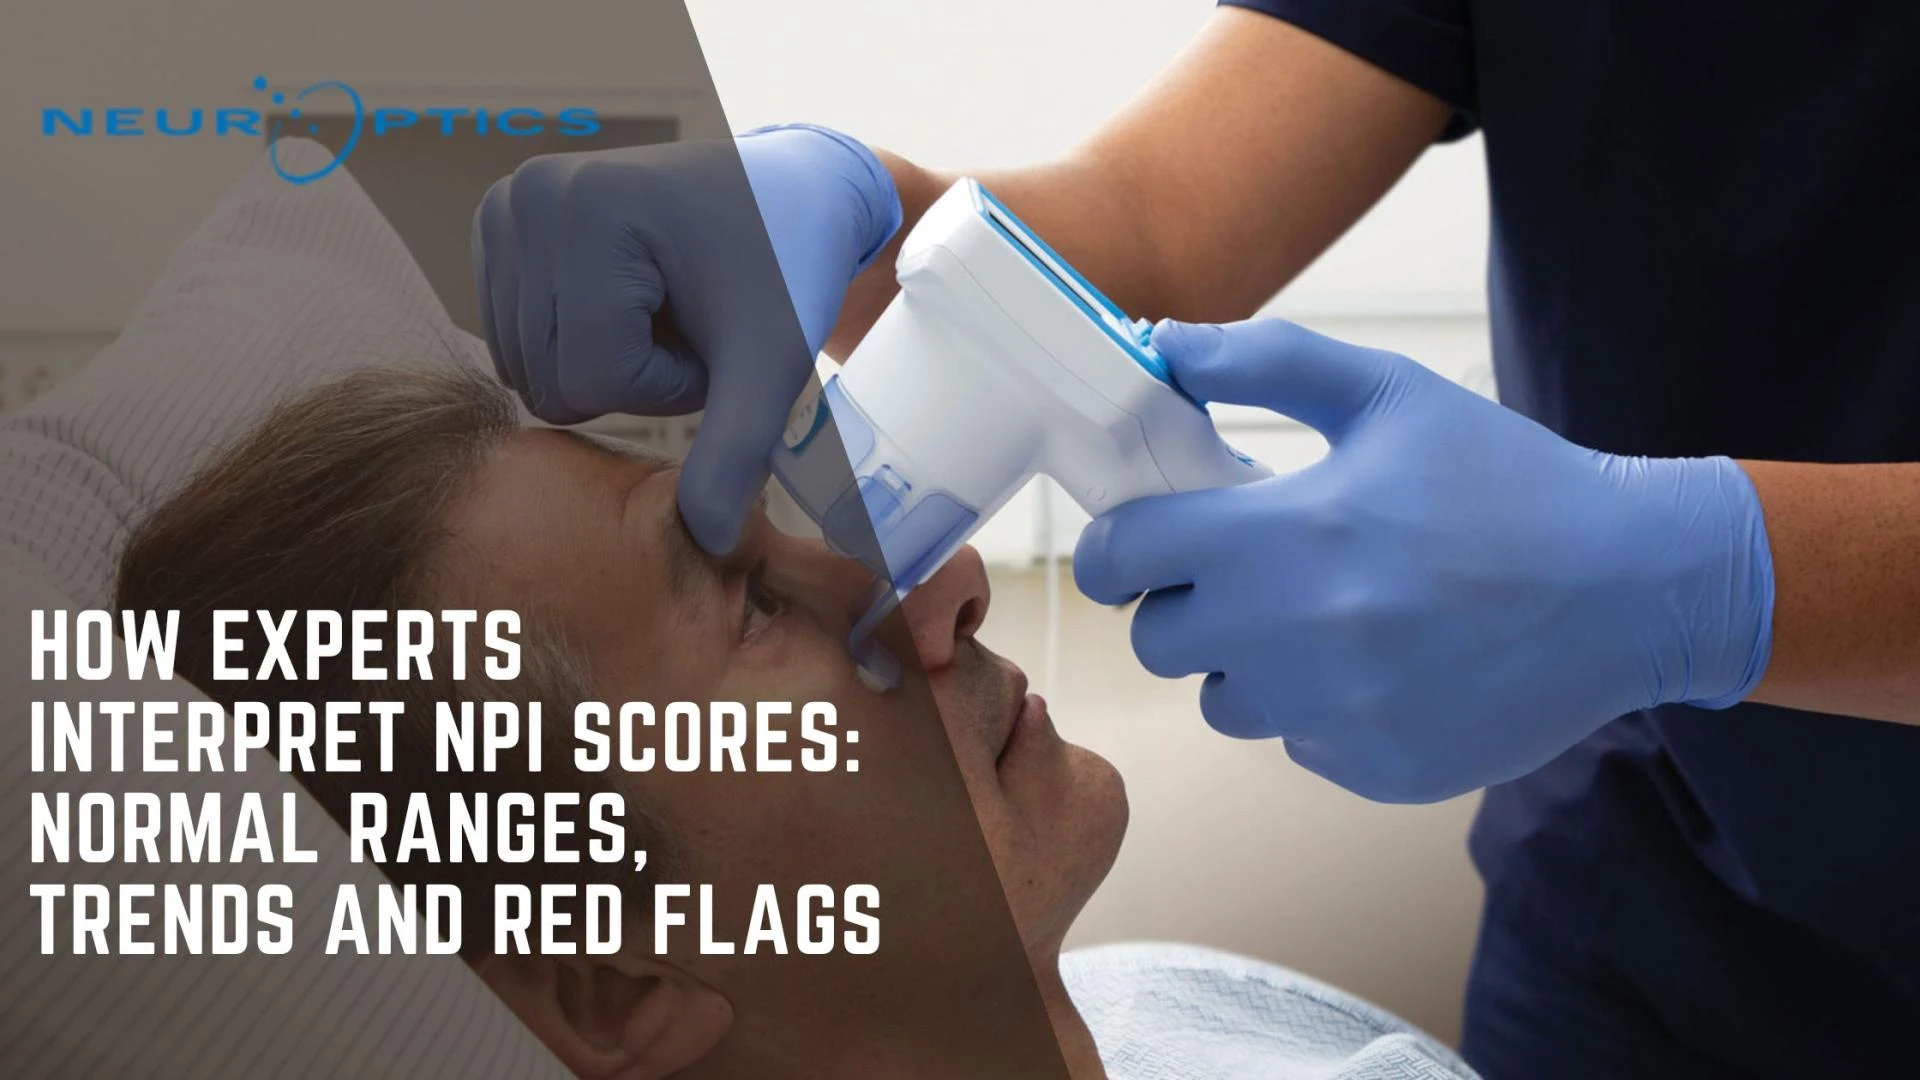
Using a pupillometer takes seconds once staffs are trained. The device rests near the eye; one measurement captures size, percent change, constriction velocity, and NPi® automatically, and the reading displays without depending on ambient lighting or examiner technique. Consistency comes from the device, which is the point of adding it alongside the neurological tools already at the bedside.
Expert Insight
The bigger practice gap usually isn't buying the device; it's building the habit of trending the numbers instead of reading them one at a time.
| Factor | Manual Penlight Exam | Automated Pupillometry |
|---|---|---|
| Objectivity | Subjective terms (brisk, sluggish, fixed) | Numeric NPi® and velocity values |
| Interrater consistency | Documented variability between examiners | Consistent regardless of who performs the exam |
| Detection of subtle change | Often misses changes under 15% | Captures small changes objectively |
| Guideline recognition | Long-standing bedside standard | Included in 2020 AHA resuscitation guidelines |
Hospitals that build this into daily workflow do three things well: standardize check frequency per unit protocol, document the NPi® trend rather than one reading, and train every shift the same way. If your unit has started comparing automated pupillometer suppliers ahead of a purchase, look for a manufacturer that trains staff on technique rather than one that just ships equipment.
Conclusion
Pupillary size, percent change, and constriction velocity each tell part of the story, and NPi® brings them together into one score a team can trust. Manual checks still matter, but the variability data makes a strong case for pairing them with an objective reading.
Ready to Standardize Pupillary Assessment on Your Unit?
NeurOptics® has built its work around the science of pupillometry, supporting critical care teams in more than 50 countries with reliable pupil data. If your hospital is evaluating how to reduce variability in neuro checks, reach out to see how NPi-based pupillometry fits your workflow.
Frequently Asked Questions
Q: What are the common causes of poor pupil reactivity?
Elevated intracranial pressure, brainstem compression, direct optic nerve injury, hypoxia, and sedatives or opioids that blunt the light reflex independent of any brain injury.
Q: How often should pupils be checked in critically ill patients?
Frequency depends on unit protocol and acuity. Many neurocritical care units check every one to two hours during higher-risk periods, more often after any change.
Q: Can pupillometry replace the full neurological exam?
No. It is one component alongside the Glasgow Coma Scale and motor response, not a standalone substitute.





















Sign in to leave a comment.