

Every amyloid looks the same down the microscope. The protein is what the examiner is really asking about.
Patrizia Fairs, Independent Medical Education Writer — NEET PG, INI-CET & FMGE I read standard textbooks and the research behind them side by side, and I flag where they disagree.
Last updated: October 16, 2026
Every pathology student can recite it: Congo red, polarised light, apple-green birefringence. Here is the awkward part. In 2024 the committee that names amyloid proteins said real slides rarely glow a clean apple-green, and it asked pathologists to say "characteristic birefringence" instead.
That small correction carries the big lesson. The stain tells you that amyloid is present; it never tells you which amyloid. For pathology questions in the National Eligibility cum Entrance Test – Postgraduate (NEET PG), the Institute of National Importance Combined Entrance Test (INI-CET) and the Foreign Medical Graduate Examination (FMGE), amyloidosis classification is by protein, and the marks sit there: where it came from, which patient makes it, and which organ it chokes. This guide compares the types side by side, the way Robbins and Harsh Mohan teach them.
Key Takeaways
- Amyloid is misfolded protein laid down outside cells as cross-beta-pleated sheet fibrils, non-branching and about 7.5–10 nm wide on electron microscopy.
- Congo red with birefringence under polarised light confirms amyloid. Thioflavin T is more sensitive but less specific.
- Amyloid is classified by protein: AL (light chains), AA (serum amyloid A), ATTR (transthyretin), Aβ2M (dialysis), Aβ (Alzheimer disease), AIAPP (type 2 diabetes), ACal (medullary thyroid carcinoma), AANF (isolated atrial amyloid).
- The kidney is the most common and most serious target, usually as nephrotic syndrome.
- A negative fat pad aspirate does not rule out amyloidosis, especially transthyretin disease.
What Exactly Is Amyloid?
Amyloid is a group of different proteins that misfold into the same shape: cross-beta-pleated sheet fibrils deposited outside cells. The precursor changes from disease to disease; the final fibril looks almost identical.
Robbins and Cotran Pathologic Basis of Disease (Kumar, Abbas and Aster, 10th edition, chapter on diseases of the immune system) describes amyloid on routine haematoxylin and eosin as an amorphous, eosinophilic, hyaline extracellular material. Harsh Mohan's Textbook of Pathology gives the same picture.
Under the electron microscope, Robbins describes continuous, non-branching fibrils about 7.5–10 nm in diameter. A clinical review by Jason Starr and Taimur Sher in Hospital Physician: Hematology/Oncology (2017) gives the same 7.5–10 nm range and notes how similar fibrils from different precursor proteins look. That sameness is the reason one stain works for all of them.
The list is long. The International Society of Amyloidosis (ISA) Nomenclature Committee's 2024 update counts 42 human amyloid fibril proteins. You need about eight for the exam.

From precursor to deposit: misfolding, beta-pleated sheet, fibril, extracellular deposit. Fibril width per Robbins (10th edition) and Starr and Sher (2017).
Is Congo Red Birefringence Really Apple-Green?
Congo red stains amyloid pink-red in ordinary light and gives birefringence under polarised light. The colour is often mixed, so the ISA now prefers the phrase "characteristic birefringence". In exam options, "apple-green birefringence" is still the expected answer.
The 2024 ISA paper, led by Joel N. Buxbaum of the Department of Molecular Medicine at the Scripps Research Institute, explains why. In real samples, "the colour varies much and there is usually a mixture of green, red, orange and yellow." Its recommendation is plain: "The committee recommends the use of a more correct description such as the neutral designation 'characteristic birefringence'."
The other stains are worth knowing because examiners like to swap them:
| Stain | What you see | Strength |
|---|---|---|
| Congo red, ordinary light | Pink-red deposits | Shows the deposit; polarise to confirm |
| Congo red, polarised light | Characteristic (classically apple-green) birefringence | Specific; the confirmatory test |
| Thioflavin T | Fluorescence under ultraviolet light | Very sensitive, not specific |
| Crystal violet or methyl violet | Metachromasia: rose-pink deposits on a blue background | Older screening stain |
| Lugol iodine (gross specimen) | Mahogany brown, turning blue with dilute sulphuric acid | Bedside gross test |
The sensitivity-versus-specificity split is old and well tested. Cooper's 1969 comparison in the Journal of Clinical Pathology found thioflavin T "very sensitive but not specific", while green birefringence with Congo red was "specific but not completely sensitive". The metachromatic and iodine reactions follow Harsh Mohan.
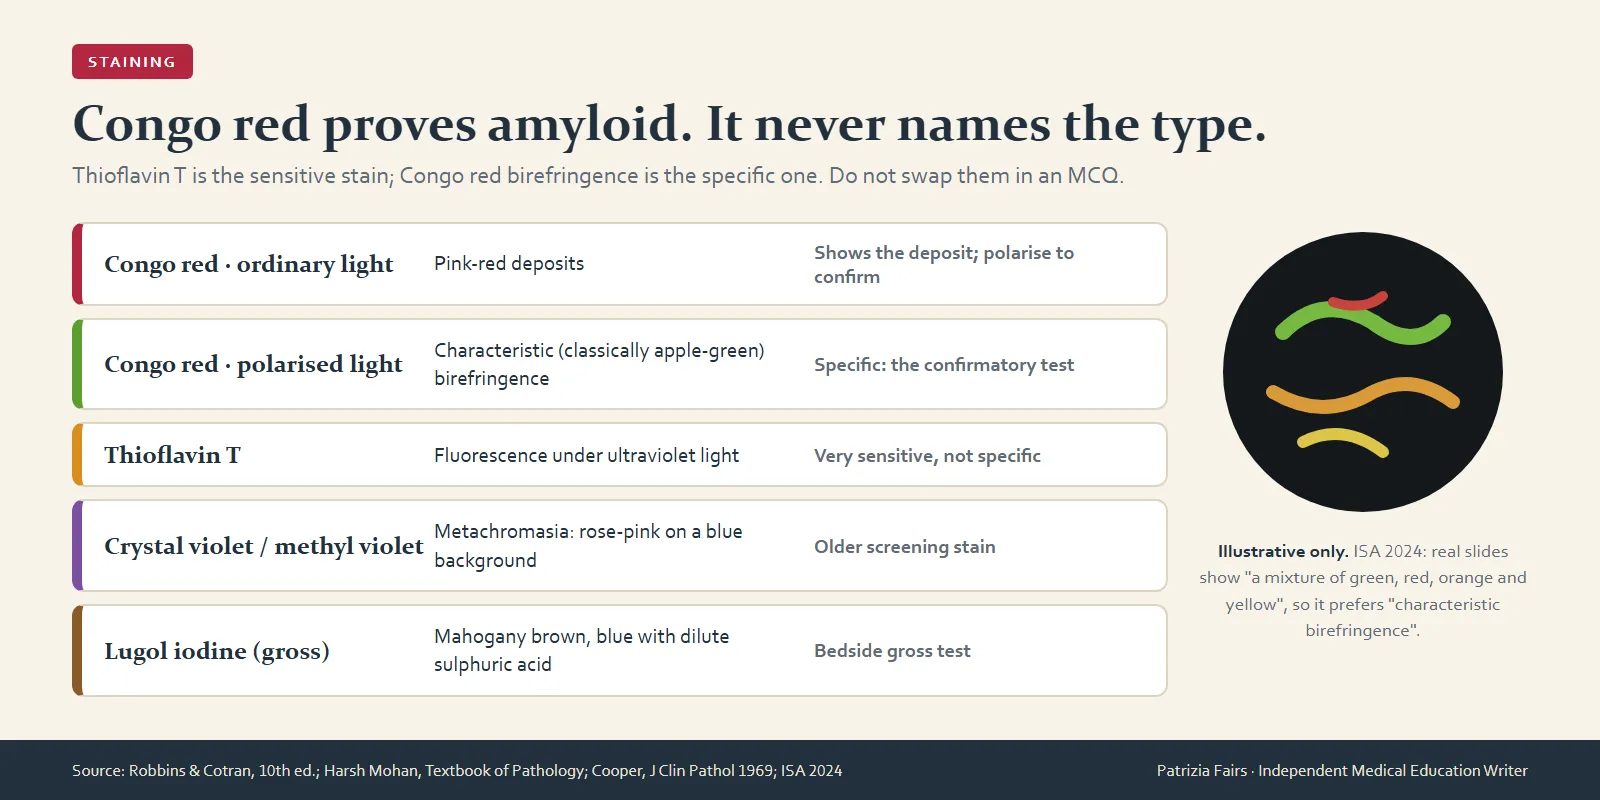
Four ways to see amyloid. Only Congo red birefringence confirms it. Sources: Robbins, Harsh Mohan, Cooper 1969 and the ISA 2024 update.
How Is Amyloid Classified by Protein?
Each type is named "A" plus the protein: AL for light chain, AA for serum amyloid A, ATTR for transthyretin. The ISA stresses that these abbreviations name the protein, so the disease is "AL amyloidosis", not "AL".
| Amyloid protein | Precursor | Typical setting | Organ clue |
|---|---|---|---|
| AL | Immunoglobulin light chain | Plasma cell dyscrasia, including multiple myeloma | Kidney, heart, tongue |
| AA | Serum amyloid A | Chronic inflammation | Kidney, liver, spleen |
| ATTR, wild type | Normal transthyretin | Older adults, mainly men | Heart |
| ATTR, hereditary | Variant transthyretin | Familial, autosomal dominant | Nerves, heart |
| Aβ2M | Beta-2 microglobulin | Long-term haemodialysis | Joints, tendon sheaths, carpal tunnel |
| Aβ | Amyloid precursor protein | Alzheimer disease | Brain plaques, cerebral vessels |
| AIAPP | Islet amyloid polypeptide (amylin) | Type 2 diabetes | Pancreatic islets |
| ACal | (Pro)calcitonin | Medullary carcinoma of thyroid | Tumour stroma |
| AANF | Atrial natriuretic factor | Isolated atrial amyloidosis | Atria of the heart |
The settings follow Robbins; the organ pattern for transthyretin and beta-2 microglobulin follows the ISA 2024 protein table. The ISA lists the atrial protein as AANP (atrial natriuretic peptide); Robbins uses AANF (atrial natriuretic factor). Either name can appear in an option.
Transthyretin is a normal blood protein that carries thyroxine and retinol (vitamin A), according to MedlinePlus Genetics. The hereditary form is autosomal dominant and affects about 1 in 100,000 people of European descent.

Eight proteins, one naming rule. Settings per Robbins (10th edition); organ patterns per the ISA 2024 protein table.
AL vs AA Amyloidosis: What Separates the Two Big Systemic Types?
AL comes from a clone of plasma cells making excess light chains; AA comes from serum amyloid A, an acute-phase protein made by the liver during long-standing inflammation. Ask what drives the protein, and the type follows.
Robbins calls AL "primary" amyloidosis and links it to plasma cell dyscrasias, multiple myeloma being the best-known. In a population study from Olmsted County, Minnesota, Robert Kyle and colleagues (Mayo Clinic Proceedings, 2019) found 1.2 cases per 100,000 person-years for 1990–2015, up from 0.89 per 100,000 in their earlier 1950–1989 series. The median age at diagnosis was 76.
AA is "secondary" or reactive amyloidosis. Robbins lists chronic infections such as tuberculosis, bronchiectasis and chronic osteomyelitis, autoimmune disease such as rheumatoid arthritis and inflammatory bowel disease, and two tumours that trip students up: renal cell carcinoma and Hodgkin lymphoma. Familial Mediterranean fever is the hereditary route to AA.
India changes the ranking. A 2009 Lung India study by Dixit and colleagues states: "Tuberculosis still remains the commonest cause of secondary renal amyloidosis in developing countries including India." A 2025 systematic review of Indian data by Mirgh, Yanamandra and colleagues, reported in Medical Dialogues, found AA more often than AL in India, with patients presenting at a median age of about 50 against about 60 in Western series.
Which Organs Does Amyloid Hit, and What Does Each Look Like?
The kidney is the most common and most serious target; the heart, spleen, liver and tongue follow in exam stems. Each has one look, per Robbins and Harsh Mohan.
- Kidney: Robbins calls renal amyloid the most common and potentially most serious organ involvement. Deposits sit in the glomeruli, and the patient presents with nephrotic syndrome.
- Heart: Stiff, infiltrated walls cause a restrictive cardiomyopathy. Subendocardial deposits can disturb conduction and cause arrhythmias. Wild-type ATTR targets the heart, mainly in older men.
- Spleen: Two patterns. A sago spleen has deposits limited to the splenic follicles (white pulp), giving tapioca-like grains on the cut surface. A lardaceous spleen has deposits in the walls of the red pulp sinuses, fusing into large map-like areas.
- Liver: Enlargement, with deposits starting in the space of Disse.
- Tongue: Macroglossia. MedlinePlus lists a swollen tongue among the symptoms of primary (AL) amyloidosis.
- Joints and wrists: Beta-2 microglobulin amyloid in long-term dialysis causes carpal tunnel syndrome.

Same organ, two patterns: follicles (sago) versus red pulp sinuses (lardaceous). Descriptions per Robbins and Harsh Mohan.
Where Should You Biopsy, and How Often Does a Fat Pad Miss?
Start with abdominal fat pad aspiration; rectal and gingival biopsies are alternatives, and the affected organ is biopsied when screening fails. The fat pad finds most AL amyloid and misses much transthyretin amyloid.
Robbins lists abdominal fat pad aspiration, rectal biopsy and gingival biopsy as the usual screening sites; MedlinePlus names the first two. On sensitivity, three well-known studies disagree:
| Study | Patients | Fat pad sensitivity |
|---|---|---|
| van Gameren et al., Arthritis and Rheumatism, 2006 | 120 with established amyloidosis (38 AA, 70 AL, 12 ATTR) | 80% on one quick smear; 93% when three smears were examined thoroughly |
| Quarta et al., European Heart Journal, 2017 | 600 with cardiac amyloidosis | AL 84%; hereditary ATTR 45%; wild-type ATTR 15% |
| Cohen et al., European Journal of Haematology, 2020 | 471 (321 AL, 150 ATTR) | AL 73.2%; ATTR 27.3% |
Why the spread? The populations differ. The 2006 series was mostly AA and AL, which deposit widely, and it rewarded careful reading of more smears. The UK National Amyloidosis Centre data in a 600-patient cardiac study found the yield in AL rose with total amyloid burden and fell sharply in wild-type ATTR. Oliver C. Cohen and colleagues at the same centre, University College London, concluded: "The sensitivity of screening biopsies in ATTR amyloidosis is poor."
For the exam, keep two points. The fat pad is the first, safest biopsy. A negative result does not exclude amyloidosis, so the next step is a biopsy of the affected organ.

Three studies, three answers: fat pad sensitivity depends on amyloid type and how hard you look. Data from van Gameren 2006, Quarta 2017 and Cohen 2020.
Which Amyloid Traps Catch Prepared Students?
Most wrong answers come from mixing up the protein with the setting. Run each stem through the same three questions: which protein, which patient, which organ.
- Dialysis patient with carpal tunnel syndrome is Aβ2M, not AL. Robbins notes that standard dialysis membranes do not filter beta-2 microglobulin out.
- AA without infection. Renal cell carcinoma and Hodgkin lymphoma can cause AA; a tumour in the stem does not automatically mean AL.
- Thioflavin T is the sensitive stain; Congo red birefringence is the specific one. Do not reverse them.
- Sago means follicles (white pulp); lardaceous means red pulp sinuses.
- Medullary carcinoma of thyroid gives calcitonin-derived amyloid (ACal) in the tumour stroma. Type 2 diabetes gives islet amyloid (AIAPP).
- Old heart, no myeloma points to wild-type ATTR, the form Robbins calls senile systemic amyloidosis.
- Amyloid is extracellular. An option placing it inside cells is wrong for these classic types.
The original trick worth taking from this guide: write a three-column card, protein → patient → organ, and fill it for the eight proteins from memory. If you can do it in under two minutes, you own the topic.
Frequently Asked Questions
Q: What is the stain of choice for amyloid? Congo red is the stain of choice. It colours amyloid pink-red in ordinary light and shows characteristic, classically apple-green, birefringence under polarised light, which confirms the deposit.
Q: What is the size of amyloid fibrils on electron microscopy? Amyloid fibrils are continuous, non-branching and about 7.5–10 nm in diameter, as described in Robbins. Fibrils from different proteins look nearly identical.
Q: What is the difference between AL and AA amyloidosis? AL comes from immunoglobulin light chains made by a plasma cell clone. AA comes from serum amyloid A, an acute-phase protein raised by chronic inflammation such as tuberculosis or rheumatoid arthritis.
Q: Which amyloid is seen in patients on long-term dialysis? Beta-2 microglobulin amyloid (Aβ2M). It deposits in joints, synovium and tendon sheaths and classically causes carpal tunnel syndrome.
Q: What is a sago spleen? A sago spleen has amyloid limited to the splenic follicles, giving small tapioca-like grains on the cut surface. A lardaceous spleen has deposits in the red pulp sinuses that merge into map-like areas.
Q: Does a negative fat pad aspirate rule out amyloidosis? No. Sensitivity ranged from 15% in wild-type ATTR to 84% in AL in one 600-patient study, so a negative aspirate with strong suspicion needs a biopsy of the affected organ.
Practise the Protein Until the Stem Gives It Away
The type is the whole question. Drill the eight proteins until the stem gives them away.
Three lines for the exam hall:
- Congo red says amyloid; the patient's history says which one.
- Dialysis means Aβ2M; chronic infection means AA; plasma cells mean AL.
- A negative fat pad is a reason to biopsy the organ, not a reason to stop.
Test the card against timed questions with these free amyloidosis practice MCQs, part of a bank of 33,500+ MCQs across all 19 subjects, free with no credit card and no daily cap.
Patrizia Fairs, Independent Medical Education Writer — NEET PG, INI-CET & FMGE I read standard textbooks and the research behind them side by side, and I flag where they disagree.
This content is for exam preparation and educational purposes only. Always refer to the official NBEMS (natboard.edu.in), AIIMS (aiimsexams.ac.in) and NMC (nmc.org.in) notifications for the latest exam pattern, dates, eligibility and cut-offs. It is not medical advice.






























Sign in to leave a comment.